When Good Numbers Hide a Bigger Story: Rethinking What Success Looks Like on Lisinopril
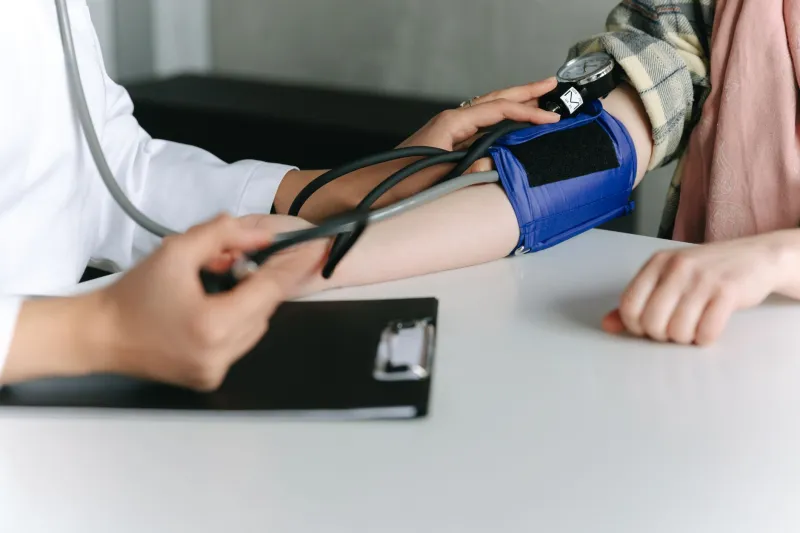
There is a moment many lisinopril patients know well. You sit down in the exam room, the cuff tightens around your arm, and the reading comes back exactly where your provider hoped it would be. The chart looks good. The conversation is brief and reassuring. You leave with a refill and a sense that everything is under control.
And yet, on the drive home, you feel exhausted. Or perhaps you stood up too quickly this morning and had to grip the counter to steady yourself. Maybe you have been sleeping more than usual, or you notice a kind of low-grade heaviness that you cannot quite name. The numbers say you are succeeding. Your body is sending a different message.
This is not a rare experience. It is, in fact, one of the more nuanced challenges in hypertension management — and it deserves a more careful conversation than a quick glance at a single reading.
The Gap Between a Metric and a Person
Blood pressure targets exist for important reasons. Decades of clinical research have established that keeping systolic pressure below 130 mmHg and diastolic below 80 mmHg significantly reduces the risk of stroke, heart attack, kidney disease, and other serious complications. Lisinopril, as an ACE inhibitor, is highly effective at helping patients reach and maintain those thresholds.
But a blood pressure number is a snapshot — one data point captured in a specific moment, under specific conditions. It tells your provider something essential about cardiovascular stress, but it does not measure how you feel walking to your car, climbing a flight of stairs, or getting through a full workday without needing to sit down.
When a patient achieves target numbers but reports persistent fatigue or dizziness, the temptation is to attribute those symptoms to unrelated causes — poor sleep, stress, aging, or lifestyle factors. Sometimes that attribution is correct. But not always.
When the Dose Is Right for the Chart, but Not for the Patient
One of the more common scenarios involves relative over-treatment. Lisinopril lowers blood pressure by relaxing blood vessels and reducing the workload on the heart. For patients whose baseline pressure was significantly elevated, a reduction to guideline-recommended targets is clearly beneficial. But for patients whose bodies had adapted over years to running at higher pressures, arriving at a lower number can feel physiologically disorienting — at least in the short term.
Orthostatic hypotension is a specific concern worth understanding. This is the drop in blood pressure that occurs when a person moves from sitting or lying down to standing upright. In patients on lisinopril — particularly those who are also taking diuretics or other antihypertensives — this transitional drop can be pronounced enough to cause dizziness, brief visual changes, or an unsteady feeling. The resting blood pressure measurement in the office may look ideal while this positional effect goes undetected.
Older adults are especially vulnerable to this dynamic, and for them, the consequences of a fall can be far more serious than the incremental cardiovascular benefit of hitting a precise numerical target.
The Quality-of-Life Conversation Your Appointment May Be Missing
American healthcare appointments are, by necessity, efficient. A primary care visit may last fifteen minutes, and much of that time is consumed by charting, refill management, and reviewing lab work. Subjective symptoms — the ones that do not show up in a reading or a blood panel — can easily fall through the cracks, particularly if the patient does not raise them directly.
This is where patient advocacy becomes a clinical tool. If you are reaching your blood pressure goals but not feeling well, that information belongs in the conversation. Consider being specific rather than vague. Instead of saying "I feel tired," try describing when the fatigue occurs, how it compares to how you felt before starting lisinopril, and whether it is interfering with daily activities. Concrete descriptions are easier for a provider to act on.
Some questions worth raising at your next appointment include:
- Is my current dose calibrated to my weight, kidney function, and other medications, or was it set as a standard starting point?
- Have you checked my blood pressure in multiple positions, including standing?
- Is my target the right one for my age and overall health profile, or is there flexibility in the guideline?
- Could any of my other medications be compounding the effects of lisinopril in a way that explains how I feel?
These are not confrontational questions. They are the kinds of inquiries that help a provider see beyond the chart and treat the full person.
Individualized Targets: A Shift in How Medicine Thinks About Hypertension
It is worth noting that medical guidelines themselves have evolved on this subject. The debate over how aggressively to lower blood pressure — particularly in older patients — has been ongoing for years. Landmark studies have produced conflicting conclusions about whether more aggressive targets produce better outcomes across all populations, or whether the benefits plateau or even reverse for certain individuals.
The concept of individualized blood pressure targets reflects this complexity. A 45-year-old with no other health conditions may genuinely benefit from tight control at 120/80 mmHg or below. A 75-year-old with a history of falls, reduced kidney function, and multiple medications may be better served by a more conservative target that preserves quality of life without meaningfully increasing cardiovascular risk.
This is not a reason to abandon blood pressure management — it is a reason to engage with it more thoughtfully. Lisinopril remains one of the most well-studied and widely recommended medications in this space, and its benefits are real. The goal is not to question whether treatment is worthwhile, but to ensure that the treatment is truly working for the individual taking it.
Tracking More Than a Single Number
Patients who want to take a more active role in their own care may benefit from maintaining a simple symptom log alongside their home blood pressure readings. Noting when dizziness occurs, what time of day fatigue is worst, whether symptoms correlate with doses, or how physical activity affects how you feel can provide a provider with a much richer picture than an office reading alone.
Home blood pressure monitors, widely available at pharmacies across the United States, can also help identify patterns that a single clinical measurement misses — including the morning surge in blood pressure that some patients experience, or the positional drops described earlier.
A More Complete Definition of Treatment Success
At LisinoprilStore, we believe that effective hypertension care is not simply about moving a number into a target range. It is about supporting patients in living well — with energy, stability, and confidence in their daily lives. Lisinopril, used thoughtfully and monitored carefully, is a powerful tool toward that end.
But tools work best when they are calibrated to the person using them. If your blood pressure is controlled and you still do not feel like yourself, that is not something to dismiss or wait out indefinitely. It is a signal worth bringing to your provider — and a conversation that has every chance of leading to a better outcome.
The numbers matter. So do you.